Register now

To access the site, please provide the required information to verify that you are a Canadian healthcare professional and create an account. Once validated, this account can be used to log in to all myAstraZeneca websites for Canadian healthcare professionals. Please use the first and last name registered with your professional college.

MATTERHORN Trial Data

Understanding IMFINZI treatment for your patients with resectable gastric or gastroesophageal junction adenocarcinoma (GC/GEJC) (Stage II to IVA)

IMFINZI in combination with fluorouracil, leucovorin, oxaliplatin, and docetaxel (FLOT) chemotherapy as neoadjuvant and adjuvant treatment, followed by adjuvant IMFINZI monotherapy, is indicated for the treatment of adult patients with resectable gastric or gastroesophageal junction adenocarcinoma (GC/GEJC) (Stage II to IVA).1

Be IN the know with IMFINZI’s MATTERHORN Trial data

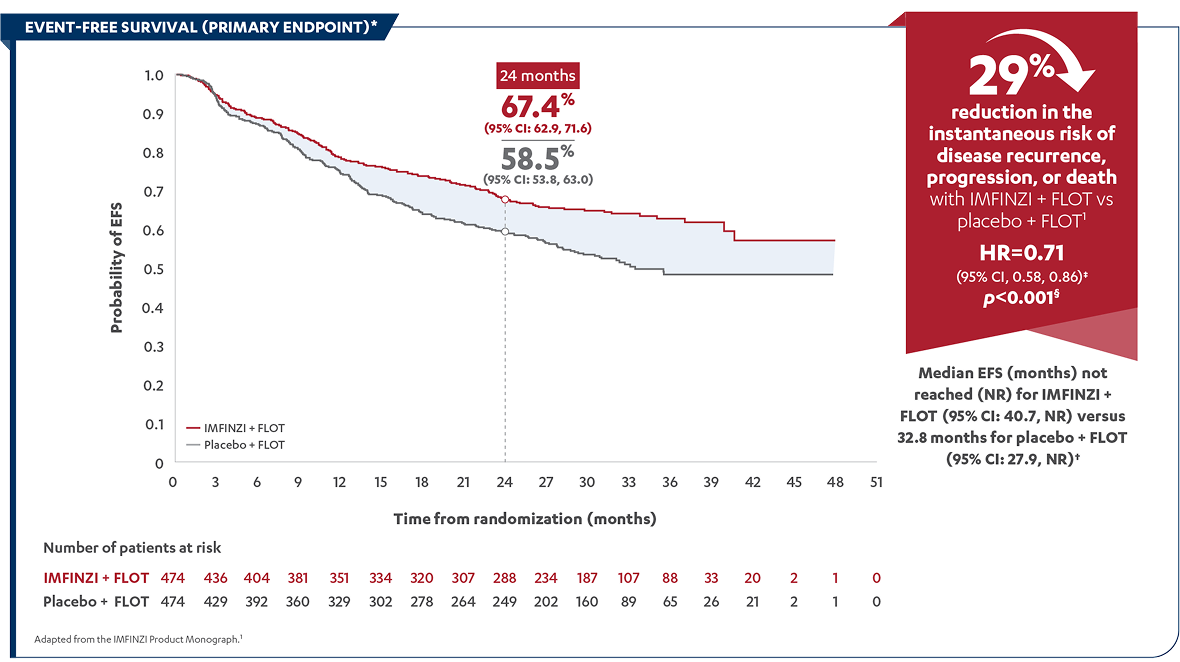
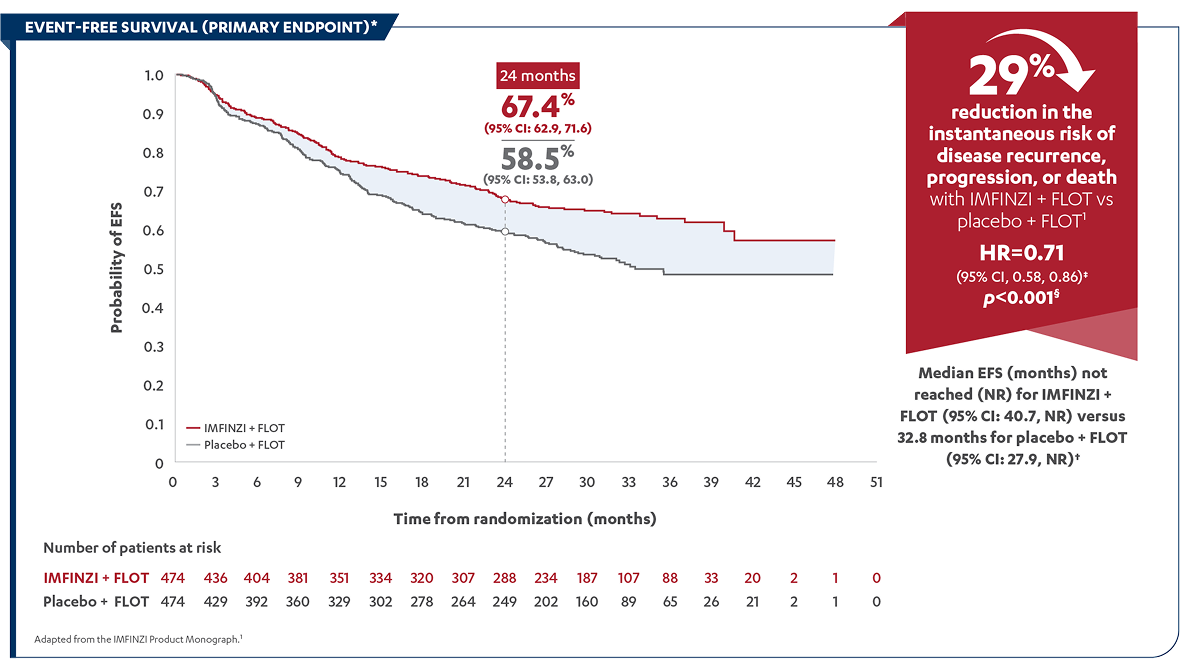
IMFINZI + FLOT Significantly Improved EFS vs Placebo + FLOT*

*EFS was defined as the time from randomization to the following, according to RECIST v1.1 per BICR assessment and/or locally by pathology testing: progression that precluded surgery or required non-protocol therapy, recurrence or progression of disease, or death due to any cause. Results are based on a pre-specified interim analysis (DCO: 20 December 2024).1
† Calculated using the Kaplan-Meier technique.1
‡ Based on stratified Cox proportional hazards model stratified by geographical region, clinical lymph node status and PD-L1 expression status at randomisation. An HR < 1 favours IMFINZI. CI calculated using the profile likelihood approach.1
§ Based on stratified log-rank test adjusting for geographic region, clinical lymph node status, and PD-L1 expression status at randomization. Based on a Lan-DeMets alpha spending function with O'Brien Fleming boundary calculated using the actual number of patients at the DCO, the boundary for declaring statistical significance of EFS was 0.0239 for an overall alpha of 5% (2-sided).1
CI=confidence interval; DCO=data cut-off; HR=hazard ratio. 

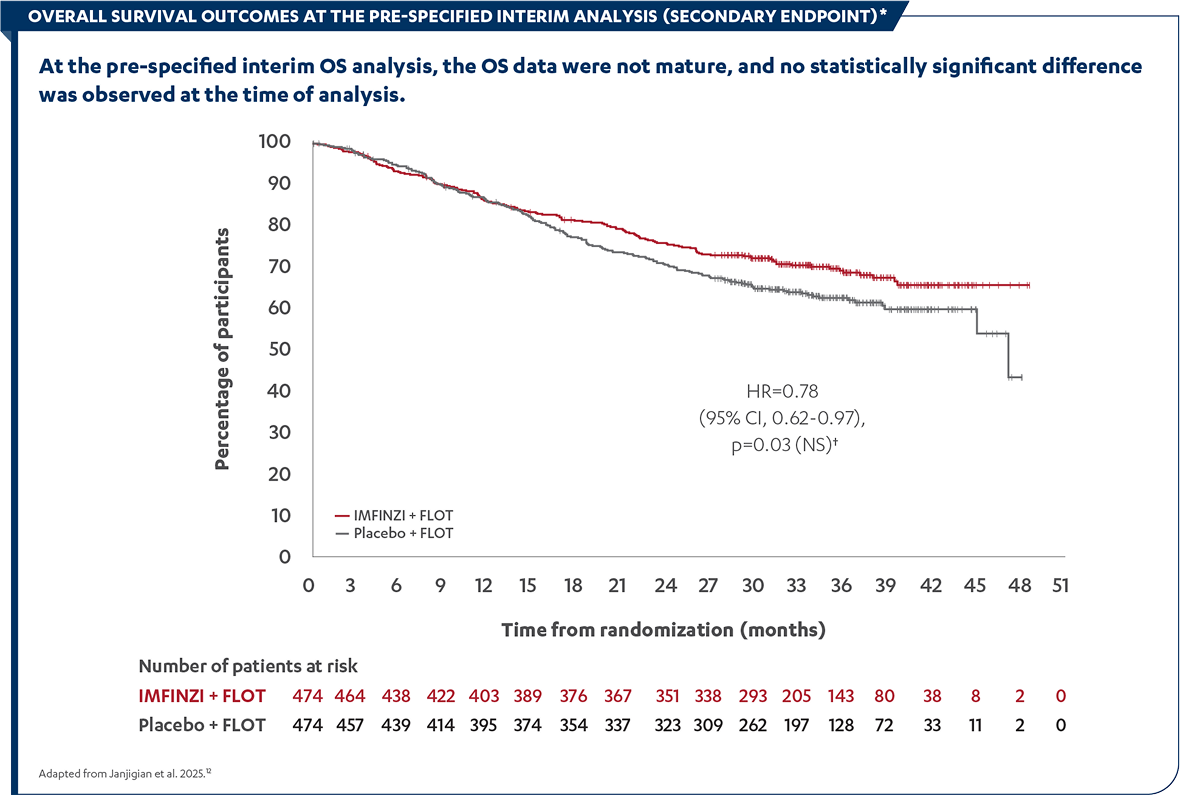
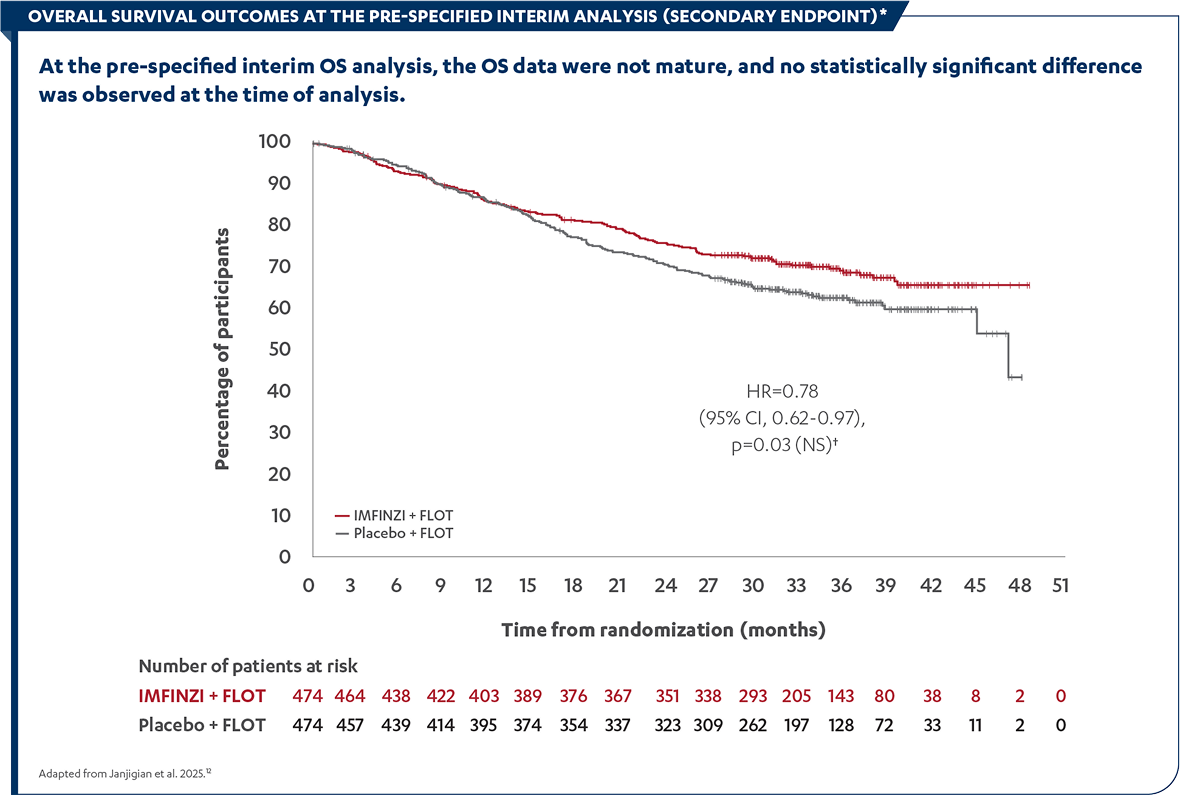
Overall survival data in MATTERHORN (secondary endpoint)1

* Overall survival was defined as the time from randomization until the date of death from any cause. Results are based on a pre-specified interim analysis (DCO: 20 December 2024).2
† Not significant. Based on unstratified Cox proportional-hazards model. The threshold of significance for this analysis was P<0.0001. The two-sided P value was calculated with a stratified log-rank test with adjustments for geographic region, clinical lymph-node status, and PD-L1 expression. Stratified log-rank test exceeded the threshold for significance (P<0.0001).2
NS=not significant.

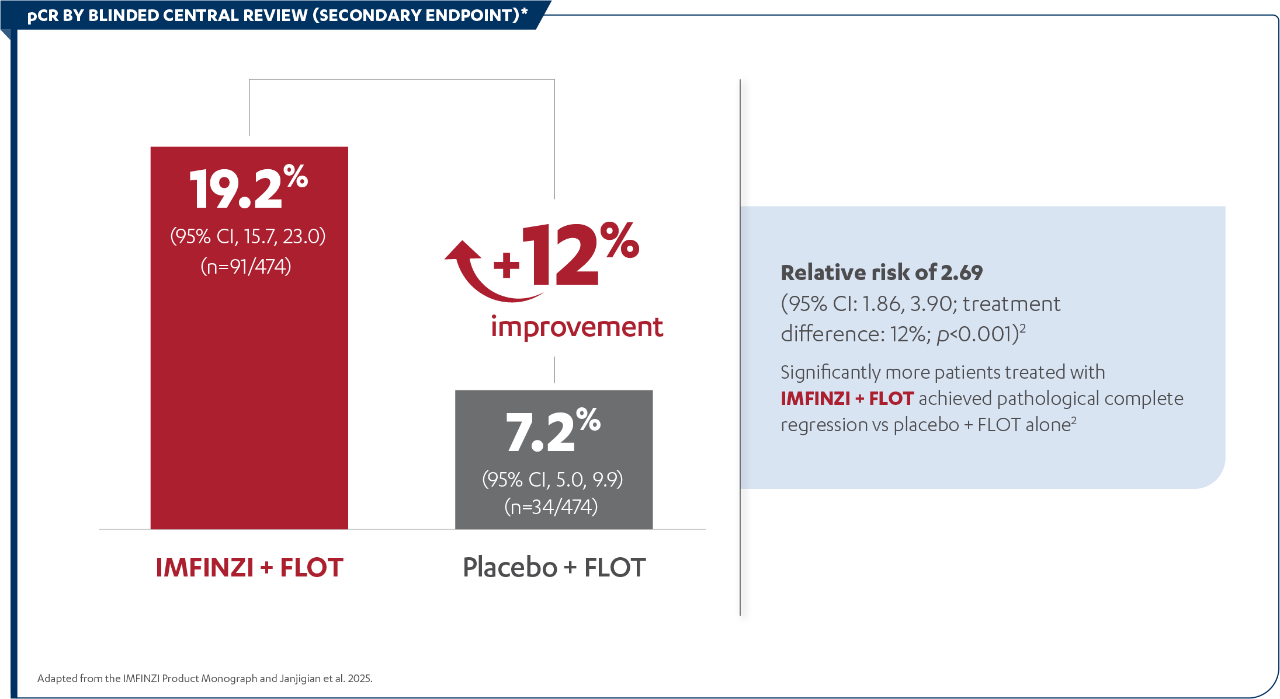
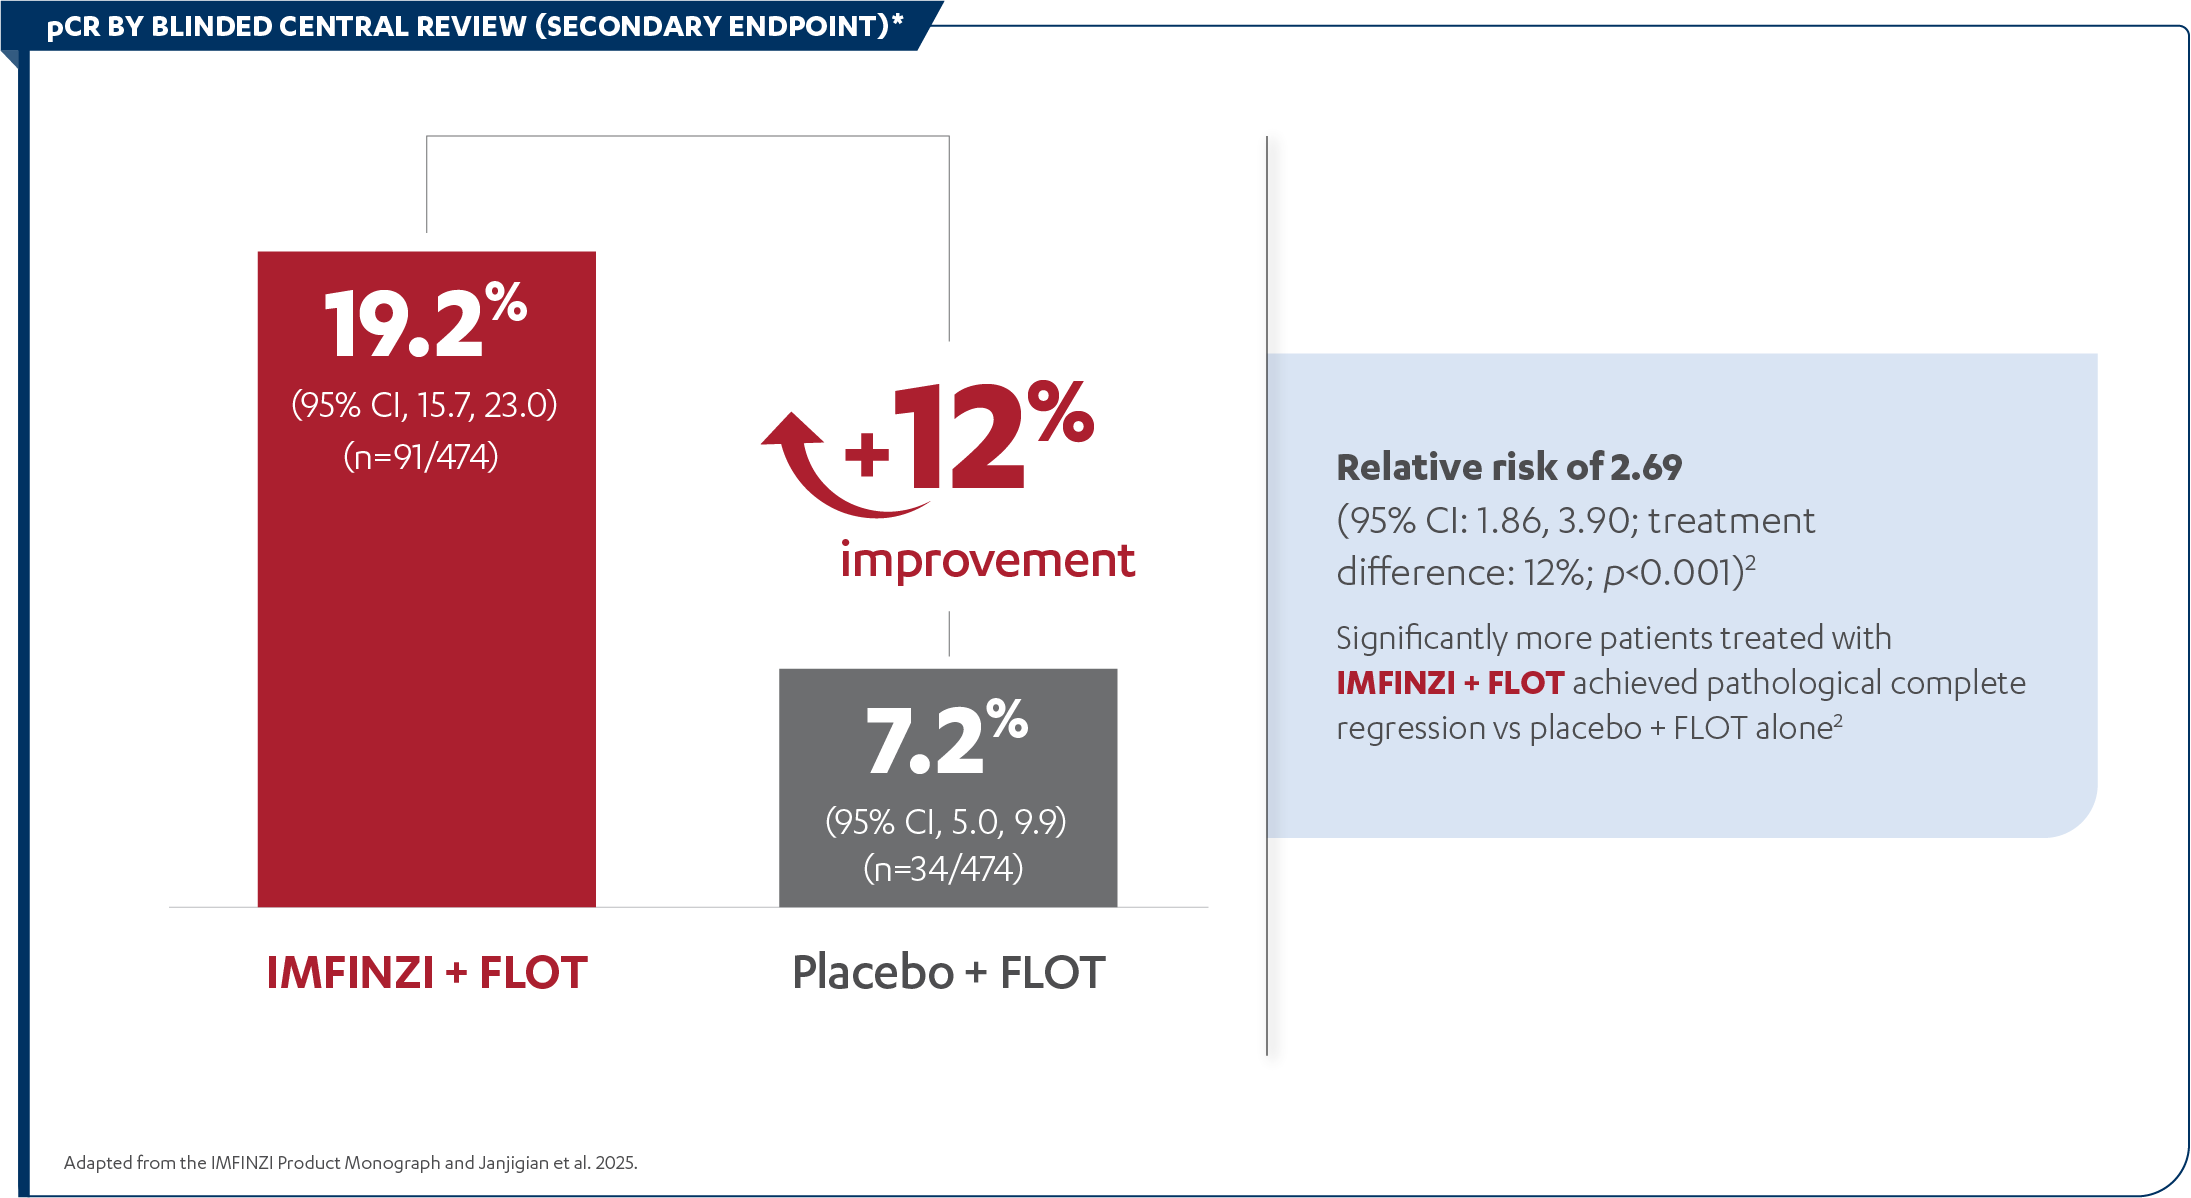
IMFINZI + FLOT more than doubled the pCR rate vs. placebo + FLOT (secondary endpoint)1

Pathological complete response rate was defined as the proportion of patients who have no residual viable tumor (100% pathological regression) found at the primary tumor and resected lymph nodes per central (or local) assessment.

*Central review of pCR was scored using modified Ryan criteria, which assess both the primary tumor and lymph nodes.
CI, confidence interval; FLOT, Fluorouracil (5-FU), Leucovorin (Folnic Acid), Oxaliplatin, Tacotaxel (Docetaxel); pCR, pathological complete response.

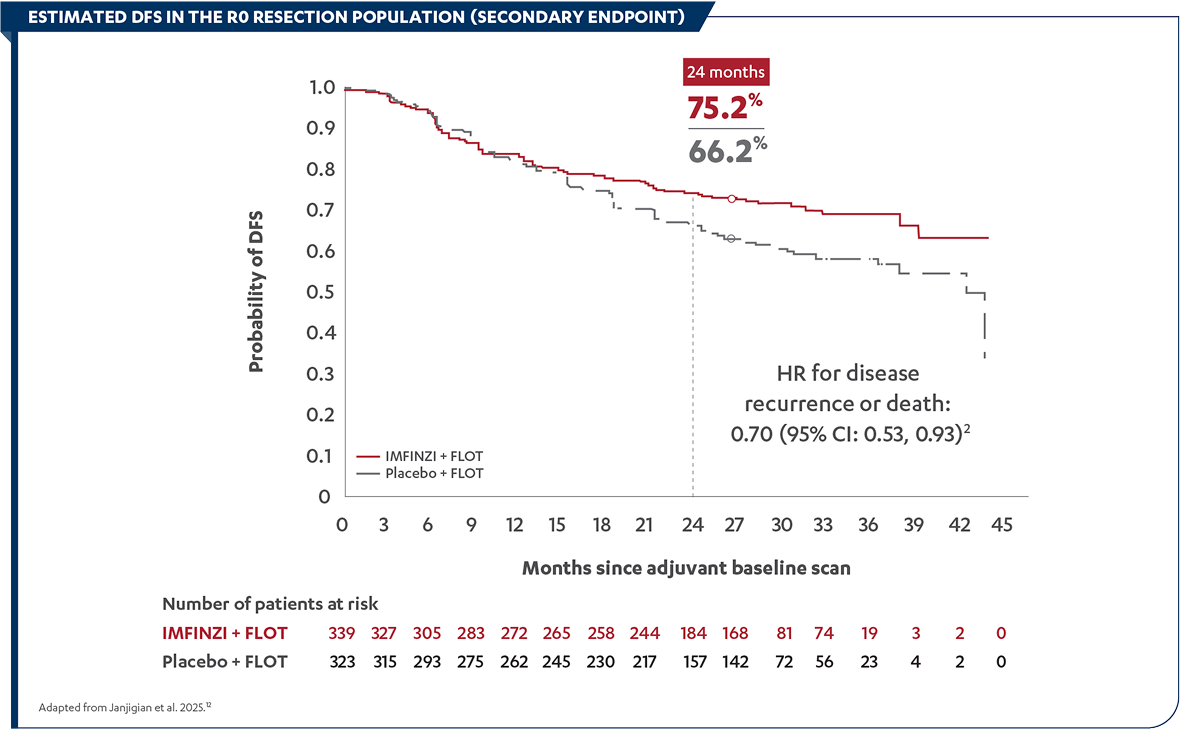
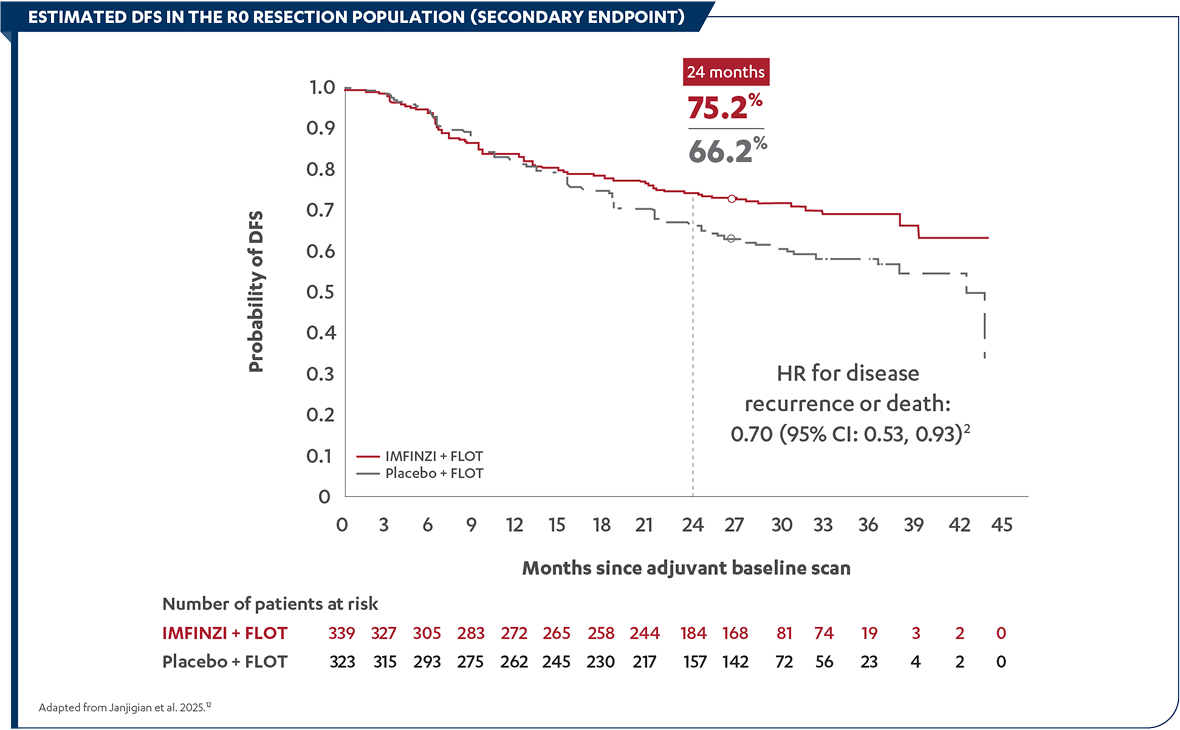
Disease-free survival (DFS) (secondary endpoint)* was longer in patients treated with IMFINZI + FLOT vs placebo + FLOT

* DFS was defined as the time from the first post-surgery scan to the first documented disease recurrence (according to RECIST, version 1.1) or death, whichever occurred first. DFS was analyzed in the R0 resection population, which included participants with margin-negative surgery and no evidence of disease on baseline imaging before the start of adjuvant therapy.1
CI: confidence interval; DFS: disease-free survival; FLOT: fluorouracil, leucovorin, oxaliplatin, and docetaxel; HR: hazard ratio; R0: no residual tumor.

MATTERHORN was a randomized, double-blind, placebo-controlled, multicentre, Phase III study designed to evaluate the efficacy of IMFINZI (1500 mg) in combination with FLOT chemotherapy as neoadjuvant and adjuvant treatment, followed by adjuvant IMFINZI monotherapy, in patients with resectable gastric or gastroesophageal junction adenocarcinoma.

IMFINZI (1500 mg) was given on Day 1 + FLOT chemotherapy on Days 1 and 15 every 4 weeks for 4 cycles (1 dose of IMFINZI and 2 doses of FLOT per cycle; 2 cycles in the neoadjuvant phase + 2 cycles in the adjuvant phase) followed by IMFINZI 1500 mg on Day 1 every 4 weeks for up to 10 additional cycles for a total of 12 cycles (1 dose per cycle) post-surgery.

Placebo was given on Day 1 + FLOT on Days 1 and 15 every 4 weeks for 4 cycles (1 dose of placebo and 2 doses of FLOT per cycle; 2 cycles in the neoadjuvant phase + 2 cycles in the adjuvant phase) followed by placebo on Day 1 every 4 weeks for up to 10 additional cycles for a total of 12 cycles (1 dose per cycle) post-surgery.

FLOT: fluorouracil (5-FU) 2600 mg/m2, oxaliplatin 85 mg/m2, docetaxel 50 mg/m2, leucovorin 200 mg/m2 was given on cycle Days 1 and 15 every 4 weeks.

The primary endpoint of the study was event-free survival (EFS) by BICR assessment and/or locally by pathology testing, defined as the time from randomization to the following: progression that precludes definitive surgery or requires non-protocol therapy, recurrence or progression, or death due to any cause. The key secondary endpoints were OS and pCR rate by blinded central pathology review.

References:

  1. IMFINZI Product Monograph. AstraZeneca Canada Inc. January 22, 2026.
  2. Janjigian YY, Al-Batran SE, Wainberg ZA, et al. Perioperative Durvalumab in Gastric and Gastroesophageal Junction Cancer. N Engl J Med. 2025;393(3):217-230. (including supplementary appendix)